K-space and reconstruction
The image before it looks like an image
In CT, the input to reconstruction is naturally described as projections: measurements along paths through the patient are organised and transformed into an image. MRI takes a different route. During readout, magnetic-field gradients make the phase and frequency of the received signal depend on spatial position. The scanner samples the combined signal, rather than measuring each image pixel independently. Those samples are arranged in k-space, a frequency-domain representation of the spatial information in the object.
For a sufficiently sampled Cartesian acquisition, an inverse Fourier transform converts the complex k-space data into an image. The coordinates in k-space are not locations in the patient. They describe spatial frequencies: how rapidly signal changes across space. This is why k-space can feel disconnected from the displayed anatomy even though it is the immediate input to reconstruction.
Spatial frequency gives a useful mental model
The simplest intuition is to treat an image as a sum of waves. Samples near the centre of k-space represent lower spatial frequencies and commonly contribute broad intensity variation, overall contrast, and coarse shape. Samples farther from the centre represent higher spatial frequencies and contribute sharp boundaries and fine detail. This is a useful first approximation, not a sharp anatomical division: structures are represented across a range of frequencies, and the exact effect depends on the sampling pattern and reconstruction.
In a Cartesian grid, the extent of sampled k-space, meaning the highest spatial frequency reached, is related to the nominal resolution. The spacing between samples, or equivalently the sampling density over a given extent, is related to the field of view. These relationships follow from sampling theory, but non-Cartesian trajectories, density weighting, partial sampling, and reconstruction assumptions make the simple centre/edge slogan incomplete. The field of view and resolution are properties of the whole acquisition and reconstruction, not of one isolated pixel.
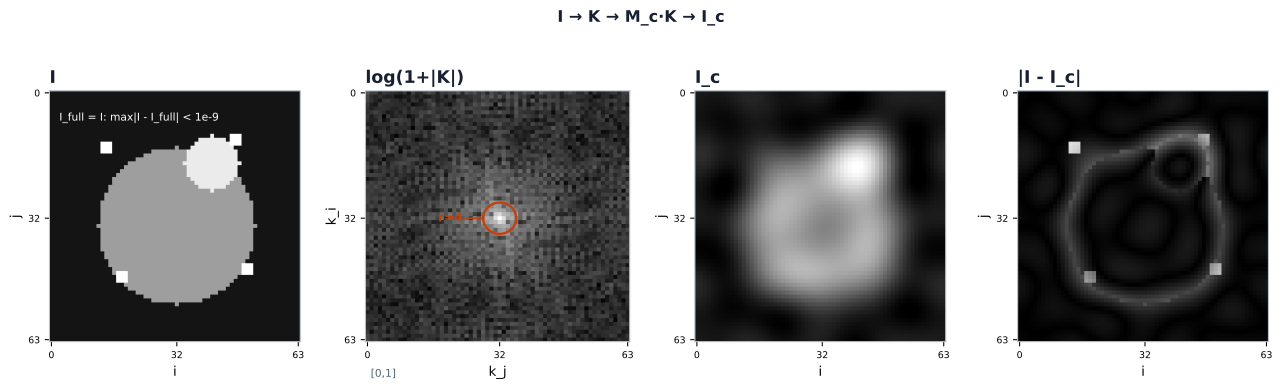
Synthetic schematic, not an MRI acquisition: there is no universal sharp centre/periphery boundary in k-space, and real sampling trajectories and undersampling masks are discrete and varied. Acceleration (parallel imaging, compressed sensing, DL reconstruction) does far more than drop the k-space periphery. Nothing shown is a quantitative MRI measurement.
The figure makes the intuition concrete. Keeping only a central low-frequency region can preserve much of the broad contrast while blurring edges and small structures. Keeping only the outer region does not produce a complete high-resolution image, because the low-frequency contribution is also needed for the image’s broad signal. The complex phase and magnitude of the samples both matter; a displayed magnitude image of k-space is a visualisation, not the data that the inverse transform consumes.
Sampling and reconstruction are part of the measurement path
Acceleration changes how k-space is sampled to shorten an examination. Parallel imaging uses the sensitivity information from multiple receive coils to reconstruct an undersampled acquisition. Compressed sensing imposes assumptions such as sparsity or structured variation. A learned reconstruction uses information learned from examples to map undersampled or otherwise degraded data to an image. These methods are not all equivalent, and none should be reduced to the claim that the scanner simply discarded the image’s edges.
Every reconstruction fills in an image under assumptions about the signal and the acquisition. Those assumptions can change apparent noise, smoothing, edge sharpness, texture, and the visibility of small structures. A learned method can produce a plausible-looking detail that is not independently supported by the sampled data, or remove a detail that its prior treats as noise. This is a reason to evaluate the method for the intended task, not a claim that every accelerated or learned reconstruction does so in the same way.
The quantitative consequence is direct. A measurement made on an image depends on the sequence, sampling pattern, reconstruction algorithm, and settings that produced it. An image reconstructed with a learned method is not automatically interchangeable with one reconstructed conventionally, even when both have the same matrix dimensions and displayed anatomy. Record the reconstruction and sampling conditions alongside the image, just as the CT chapter records its reconstruction kernel.
Once image formation is understood as a chain that includes acquisition and reconstruction, the next question is how a model behaves when one link changes. That is acquisition- driven domain shift.
Sources
- Stanford Medicine Body MRI Research Group, MRI Physics Education Materials — public visual orientation on MRI image formation, spatial frequency, k-space, resolution, and field of view.
- Ridgway JP. Cardiovascular magnetic resonance physics for clinicians: part I. J Cardiovasc Magn Reson. 2010;12:71. doi:10.1186/1532-429X-12-71. (Full text)
- Larson P. Principles of MRI: The MRI Signal Equation. Educational resource, 2025. doi:10.5281/zenodo.5547020. (Technical reference)
- Moratal D, Valles-Luch A, Marti-Bonmati L, Brummer ME. k-Space tutorial: an MRI educational tool for a better understanding of k-space. Biomed Imaging Interv J. 2008;4:e15. doi:10.2349/biij.4.1.e15. (Full text)
- Heckel R, Jacob M, Chaudhari A, Perlman O, Shimron E. Deep learning for accelerated and robust MRI reconstruction. Magn Reson Mater Phy. 2024;37:335-368. doi:10.1007/s10334-024-01173-8. (Full text)
© 2026 Adrian Tkacz · BioMedical-IT
Original text and figures are licensed under the Creative Commons Attribution-NonCommercial 4.0 International License (CC BY-NC 4.0), unless otherwise noted. Please credit Adrian Tkacz / BioMedical-IT and link to the original source. Third-party materials retain their respective rights and licenses.